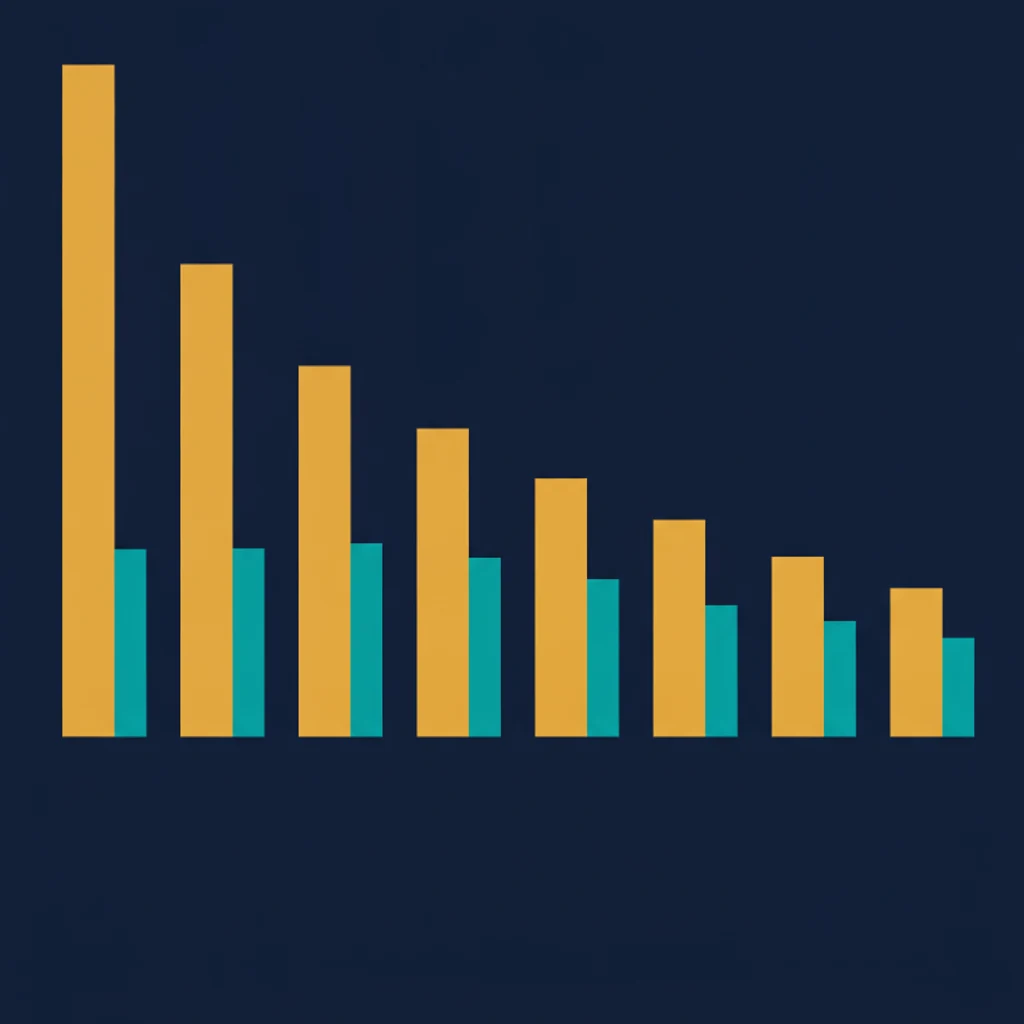
A hernia repair bills 8.9 times what Medicare actually pays hospitals to perform it. A cataract surgery bills 8.0 times Medicare's rate. Open-heart surgery, by comparison, bills only 5.7 times.
The counterintuitive pattern: simpler outpatient-convertible procedures consistently carry higher markup ratios than complex cardiac surgeries — even though the absolute dollar amounts skew the other direction. Understanding why requires a look at how hospital billing and Medicare payment actually interact.
The numbers below come from CMS Medicare 2023 provider utilization data — the same facility-level charge data that powers every procedure cost table on this site. For each of the 8 procedures below, we have verified procedure code mappings and hospital-level billed charge versus actual Medicare payment records from 800 to 3,800 facilities per procedure.
The Markup Ranking, Ranked by Ratio
The table shows mean billed charges, mean Medicare payments, and the markup ratio (billed ÷ Medicare paid) across 8 common procedures with verified CMS code mappings. The "absolute gap" column shows the dollar difference that sets the negotiation floor for uninsured and out-of-network patients.
| Procedure | Hospitals | Mean Billed | Medicare Pays | Markup Ratio | Absolute Gap |
|---|---|---|---|---|---|
| Hernia Repair | 3,840 | $49,137 | $5,551 | 8.9× | $43,586 |
| Cataract Surgery | 1,862 | $17,089 | $2,146 | 8.0× | $14,943 |
| Gallbladder Removal | 810 | $95,426 | $13,229 | 7.2× | $82,198 |
| Hip Replacement | 3,691 | $62,263 | $8,500 | 7.3× | $53,763 |
| Heart Bypass (CABG) | 1,435 | $265,380 | $40,129 | 6.6× | $225,251 |
| Knee Replacement | 3,686 | $79,812 | $12,236 | 6.5× | $67,576 |
| Pacemaker Implantation | 1,482 | $118,806 | $19,809 | 6.0× | $98,998 |
| Open-Heart Surgery | 808 | $345,067 | $60,641 | 5.7× | $284,425 |
Source: CMS Medicare Provider Utilization and Payment Data 2023 (IPPS + OPPS). Figures are means of per-hospital averages. All procedures use verified DRG/APC code mappings.
Why Simple Procedures Get Billed More Aggressively
The ratio pattern holds across all 8 procedures, but it isn't obvious why hernia repairs would carry a higher markup multiplier than open-heart surgery. Three mechanisms drive it.
1. The denominator effect: Medicare pays more for complexity
Medicare's Diagnosis-Related Group (DRG) payment system sets reimbursement based on procedure complexity, resource use, and expected length of stay. A heart bypass generates a Medicare payment of roughly $40,000 per case. A hernia repair generates roughly $5,500. Both payments are calibrated to cover actual delivery costs.
Hospital chargemaster prices — the gross "sticker" figures in this table — were not set the same way. Chargemasters evolved over decades without a standardized formula. When hospitals set a hernia repair at $49,000 and Medicare pays $5,500, the ratio is 8.9×. When they set open-heart surgery at $345,000 and Medicare pays $60,000, the denominator is already so large that even a generous absolute markup compresses the ratio to 5.7×.
2. Cross-subsidization: outpatient procedures as profit centers
Many health economists have documented hospitals' practice of using high-volume, lower-acuity procedures to subsidize complex inpatient care, which often runs at thin margins or losses under DRG-fixed payments. Cataract surgery and hernia repair are among the highest-volume outpatient procedures — a hospital doing 2,000 cataract cases per year has strong incentive to maintain a high chargemaster baseline for that line, particularly when billing out-of-network insurers or uninsured patients.
3. Price elasticity and cash-pay exposure
Patients facing elective outpatient procedures are more likely to be uninsured, underinsured, or dealing with high-deductible plans than patients undergoing emergency cardiac surgery. That cash-pay exposure — where chargemaster prices directly set the negotiating floor — gives hospitals more pricing latitude on lower-acuity procedures. An uninsured patient facing a $49,000 hernia bill has less leverage than a cardiac surgery center negotiating annual contracts with major insurers.
What the 2025 JAMA Surgery Study Adds
The markup ratios above are national averages across all facilities. A September 2025 study in JAMA Surgery (Sakowitz et al.) examined a different lens: what happens at the highest-markup hospitals for complex elective procedures?
The researchers found that hospitals in the top decile for markup apply a median of 8.5× — and up to 17.5× — over actual costs even for major elective operations like coronary artery bypass grafting, colectomy, and hip replacement. That is: the counterintuitive pattern observed in national averages flips at high-markup outlier facilities, where complex procedures are also subjected to extreme billing inflation.
The two findings are complementary, not contradictory. Nationally, simpler procedures tend to carry higher average markup ratios. But at hospitals with aggressive pricing cultures, any procedure type can be marked up to extreme levels. The chargemaster is ultimately a hospital-level policy decision, not a procedure-level one.
A Methodological Caveat: IPPS vs. OPPS Data
The table above mixes two CMS payment systems. Hernia repair and cataract surgery draw primarily from outpatient APC (Ambulatory Payment Classification) data; knee replacement, hip replacement, open-heart, heart bypass, pacemaker, and gallbladder removal draw primarily from inpatient DRG data. The two systems bundle costs differently — inpatient DRGs include room, board, and ancillary services in a single payment, while outpatient APCs may separately bill certain drugs, devices, or anesthesia.
This means the markup ratios are not perfectly apples-to-apples across the two settings. What the table captures reliably: the relative scale of billed charges versus Medicare's own payment determination, which is the relevant signal for anyone trying to understand why hospital bills are so large relative to what those procedures actually cost to deliver.
What This Means for Self-Pay and Out-of-Network Patients
The chargemaster rate is not what most patients pay. Commercial insurance negotiates rates that, per the RAND Hospital Price Transparency Study (Round 5, 2024), average 254% of Medicare nationally — substantially below the 570%–890% range in this table, but still well above Medicare's own payment. The gap between chargemaster and negotiated rate is typically absorbed by the insurer.
Self-pay patients face a different picture. The CMS Hospital Price Transparency Rule requires hospitals to post discounted cash prices alongside chargemaster rates — those cash prices are typically 40–60% of chargemaster and represent the realistic out-of-pocket floor for uninsured patients. Under the No Surprises Act, providers must also supply a Good Faith Estimate before any scheduled procedure for uninsured and self-pay patients.
The practical implication of the markup ranking: because hernia repair and cataract surgery carry the highest ratios, uninsured patients facing those procedures face the widest gap between the chargemaster figure and the actual cash price. Asking for the discounted cash price upfront — before any billing is processed — is more important for these procedures than for high-complexity cardiac cases, where the absolute dollar amount is larger but the provider has already priced the case carefully against insurance contracts.
For elective procedures where the site has full hospital-level data — including price ranges within the same metro area and how dramatically individual hospitals vary — those per-hospital differences typically exceed the procedure-level markup pattern shown here. The same hernia repair at two hospitals in the same city can vary by 10× in billed charges, even though the category average sits at 8.9×.
The Bottom Line
National average CMS data from 17,000+ hospitals shows a consistent pattern: simpler outpatient-convertible procedures carry higher billed-to-Medicare-paid ratios than complex cardiac surgeries. Hernia repair at 8.9× and cataract surgery at 8.0× sit at the top; open-heart surgery at 5.7× and pacemaker implantation at 6.0× at the bottom. The mechanism is a combination of how Medicare's DRG payment system sets higher absolute rates for complex care, how hospitals use high-volume outpatient procedures as profit centers, and how cash-pay exposure differs by procedure type.
The markup ratio tells you where the chargemaster starting point is most inflated — which determines how aggressively you should ask for a cash discount, request itemized billing, or negotiate before a scheduled procedure. It does not determine what you'll actually pay; your insurance network, income, and hospital financial assistance eligibility do that.